Your guide to

Preparing for egg freezing

Wherever you are in your journey, from first wondering about egg freezing to your first, second or next cycle, this guide is here to answer your questions on all things egg freezing. About 22 minutes to read.

Written and edited by fertility specialists: Navya Muralidhar and Dr Vivienne Hall. No email, no sign-up.
Illustration of an egg freezing medication pen beside a petri dish with three glowing eggs
Introduction

Egg freezing has become quite the talk of the town

With celebrities doing it, news reports and magazines covering it, and people sharing their experiences on it, you’re left to wonder: what’s all this about?

It may sound intimidating, the talk around fertility, testing, appointments, the process. But we’re here to tell you: it’s only because it’s not talked about enough.

The point is: egg freezing is not just a hushed topic anymore. It’s a reproductive choice.

It’s for women who want to voluntarily preserve their fertility. It’s for the LGBTQ community, to freeze eggs or go for donor eggs to start their family. It’s a mandatory task for women undergoing chemotherapy. It’s advised for women before their endometriosis surgery.

And regardless of where you are in your journey, be it your first cycle, or last, this guide is here to answer your questions, on all things egg freezing.

So, grab that cup of coffee and read on!

Medically reviewed by Dr Vivienne Hall, Fertility Specialist.

Egg freezing 101

I’m new to egg freezing. Where do I start?

Welcome to the “our reproductive choices, our own terms” club.

Apart from that, it’s also about what’s not discussed enough: that there is a natural decline in fertility with our age. As we hit our late 20s and 30s, the number and the quality of eggs in our ovaries begin to decline. And rather than panic about it, it’s time to sit back and think about your reproductive health.

Are you okay with not having a family in the future, or are you in the “maybe” or “thinking about it” boat? That’s where egg freezing comes in.

The egg freezing process in the UK

Egg freezing helps you save a number of eggs at good quality for fertilisation and family planning later on (AKA, when you’re ready to start a family). That’s right. No partner. No need for a sperm donor. Just you and your health choices.

It involves a series of blood tests that check your hormonal levels. Post that, you undergo a week or two of hormonal medication that helps grow multiple eggs in your ovaries (versus the normal “one egg of the month”). As the last step, you undergo egg retrieval, where they aspirate and freeze your eggs in the laboratory, done by embryologists.

1

Initial consultation

Discussing your individual circumstances, goals and expectations with a qualified fertility specialist. This initial meeting is important as it helps your healthcare provider curate a personalised plan and address any specific concerns you might have.

2

Medical evaluation

You may be tested for hormones such as anti-Müllerian hormone (AMH), which helps you assess egg reserve, ultrasound tests such as antral follicle count, and hormones such as FSH and LH to assess your ovarian reserve and overall fertility health. These tests provide valuable insights into your egg quantity and quality, informing the most suitable approach for your individual needs.

3

Stimulation phase

Fertility medications are administered to stimulate the development of multiple eggs within your ovaries. This phase typically involves daily injections such as gonadotropins for a specific duration, as determined by your doctor based on your individual response and the overall treatment plan. The final step of the stimulation plan is the trigger (hCG), which is given 36 hours before egg retrieval. This helps mature the egg right in time for retrieval.

4

Egg retrieval procedure

A minimally invasive procedure performed under light sedation or anaesthesia to collect mature eggs for freezing. This brief procedure allows gynaecologists to puncture the follicle and extract the eggs from the ovaries, which are then sent to the laboratory for further processes.

5

Cryopreservation

The retrieved eggs are frozen using vitrification techniques for long-term storage. One such device used to freeze is called a cryolock, which is a thin device with a cap. One cryolock can hold about 2–3 eggs. This process effectively preserves the eggs, by dipping the cryolocks in liquid nitrogen containers, allowing them to be thawed and used for future fertilisation attempts when you’re ready to use them.

What if I want to use my frozen eggs?

When you’re ready to use your frozen eggs, you just have to give the clinic a call. You will then be tested for hormones, and based on your stage of the menstrual cycle, your healthcare provider will personalise an embryo transfer protocol for you.

We like to split this part into two stages:

  • The laboratory stage: this involves several crucial steps when it comes to identifying and preparing the egg for intracytoplasmic sperm injection (ICSI).
  • The embryo transfer stage: this refers to the steps taken from preparing the uterus to transferring the embryo and confirming a pregnancy.

The laboratory stage

  • You may ask to use your frozen eggs if you have a sperm donor sample or your partner’s sperm sample.
  • The embryologist identifies the cryolock that has your frozen eggs, and prepares to warm them.
  • After that, each egg is fertilised with one sperm to create an embryo via ICSI (intracytoplasmic sperm injection) and not IVF (in vitro fertilisation).

Why ICSI instead of IVF?

IVF mimics natural fertilisation in a way, but happens in the lab, where eggs and sperm are incubated together in media overnight, and checked for fertilisation. During IVF, the eggs are left intact with the cells around them, which play a key role in allowing only one sperm to fertilise the egg, just as it happens naturally.

But with frozen eggs, the cells outside the egg are removed before freezing. Once the egg is “nude” or stripped of its protective jacket, you risk multiple sperm entering the egg if IVF were to be done. To avoid that, ICSI is done, such that one sperm is injected at a time.

The embryo transfer stage
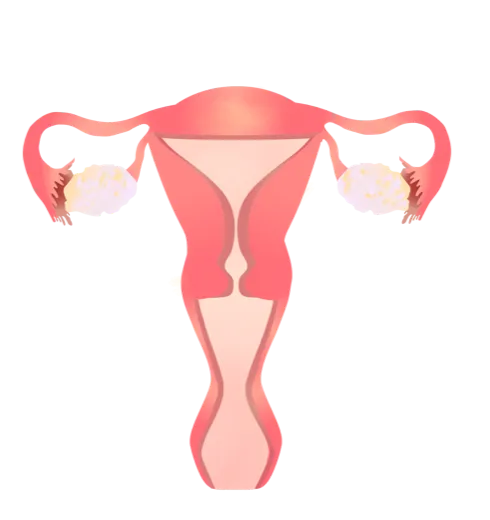
Illustration of the uterus, fallopian tubes and ovaries
  • At this stage, the embryo is at day 5/6/7. Most clinics transfer day 5 embryos, and day 6 or day 7 embryos can be frozen for future use.
  • By now, you would have ideally had a medicated protocol to prepare your uterus for this transfer. The medication is to ensure that the uterine lining is thick and supportive of this new member (the embryo).
  • The gynaecologist takes a flexible, smooth device called a catheter to insert the embryo into the uterus (around the fundus).
  • And next? We hope for implantation to occur and for the embryo to be nested in its cosy new home.

Around 15 days later, you may be asked to take a beta hCG test, to confirm pregnancy.

I’ve heard about egg freezing

I’ve heard all about egg freezing, and I want to explore this option. Where do I start?

You’ve done your homework, given it a lot of thought, and now you’re curious about how to start exploring egg freezing. The decision-making process can be overwhelming, perplexing, and even daunting.

Do I consult my GP? Should I book an appointment online? Should I search around for the best fertility clinic? This is where Sophie Hermann found herself too, at one point:

“So here I was at 36, still mulling over this decision. I’d been wrestling with these thoughts for a good four years. The big questions were: Where do I start? How long will it take? What’s the cost? And let’s not forget the big one – is it going to hurt?”

Sophie Hermann, 36

Understanding your egg reserve

Understanding your egg reserve and hormonal levels is the first step in the egg-freezing process.

Our ovaries contain follicles which help house, grow and mature eggs every month. These growing follicles produce anti-Müllerian hormone (AMH), which can be measured via a simple blood test.

This helps provide valuable insights into your ovarian reserve, helping your healthcare provider or GP gauge your egg yield number or reserve and the potential steps to take if you opt for an egg-freezing cycle.

1-1 consultations

A 1-1 consultation is an interactive session that allows you to ask questions, discuss your individual circumstances, and receive tailored guidance. This can help you decide on whether egg freezing is for you or not, and provide clarity as you move forward.

Choosing a clinic

With so many options out there, it can be overwhelming to find the one that fits your needs. How do you choose the right clinic out of so many options? Is it worth switching if you’re not getting on with your current fertility doctor? Here are some factors to consider when choosing an egg freezing clinic.

1

Clear success rates

We suggest learning about different types of success rates, and understanding how different clinics talk about their success rates. You’ll see “live birth rates” used regularly as this is the end goal most women are thinking of.

2

Location

Often several visits are needed as part of a treatment, so make sure the clinic’s location is convenient.

3

Cost

You might be able to afford the top fertility clinic, regardless of price. Or you may be on a tighter budget. Either way, cost vs quality is a key point to think about. For today’s real prices at the clinics we’ve met, see Compare prices →

4

Your instinct

Don’t forget, choosing a fertility clinic is a personal decision. What works for someone else may not work for you. Do your research. Trust your instincts.

5

Staff and facilities

Knowledgeable and caring staff make all the difference. It’s a lot easier to talk about fertility when you feel comfortable. Kind, qualified clinic staff and modern, up-to-date facilities will give you a better overall experience.

6

Services offered

Whilst choosing a location to freeze and store your eggs, it’s helpful to know whether they offer intracytoplasmic sperm injection (ICSI), the technique used to fertilise frozen eggs when the time comes.

Your next step

Choosing a clinic?

Start with a free 15-minute call with a couple of clinics you like, then compare what’s included and the real total.

Medical evaluation
Illustration of a clipboard and stethoscope

It can be scary to think about all that is to come, but we want to remind you that you’re doing this for future you. And that you’ve got this.

At this stage, you’ve had a chat with your GP, visited a clinic, decided that egg freezing is for you, and are at the first step of your egg freezing cycle. Here is a deep dive of the first step.

1

Hormone testing

Your doctor will likely recommend hormone testing, including anti-Müllerian hormone (AMH) and follicle-stimulating hormone (FSH) levels. These tests help provide valuable insights into your ovarian reserve, helping your healthcare provider decide the most suitable approach for your individual needs.

2

Ultrasound scans

Pelvic ultrasounds are often used to assess the antral follicle count (AFC), which reflects the number of small follicles in your ovaries that have the potential to develop into mature eggs. This information, combined with your hormone levels, helps your doctor personalise the stimulation protocol for your cycle.

3

Cycle preparation

Discuss with your doctor whether a 3-month pre-cycle preparation period is recommended or if you can get started straight away.

Questions to ask your doctor during your medical evaluation

What does it mean if my AFC is low or high?

Antral follicle count (AFC) is basically an ultrasound visualisation of the number of follicles on the surface of the ovary that month.

A group of follicles every month are selected to release the “egg of the month”, and a high or low AFC means the same as a high or low AMH because it is the pre-antral follicles which produce AMH.

So a low AFC indicates a low egg reserve and a high AFC might be described as a polycystic ovary.

What does it mean if my AMH is low or high?

If your AMH (anti-Müllerian hormone) is low, it usually indicates a declining egg reserve (low number of eggs left in your ovaries).

If your AMH is high (in cases such as PCOS) it could mean that you retrieve more eggs during an egg freezing cycle, but it is also a risk factor for conditions such as OHSS.

Does my follicle number mean that I get the same number of eggs?

As a general rule, the antral follicle count is a good indicator of the number of eggs you will get.

To be precise, when undergoing stimulation for egg freezing, you may be given an estimate of follicles that are in the 16–22mm range, which are said to be more indicative of having a mature egg.

Why do I need routine blood tests as well?

You need routine blood tests including virology screening because your eggs will be stored in a laboratory. Any human tissue or sample being handled and kept in storage has these legal requirements to be screened for hepatitis B, C and also HIV.

You will also have a full blood count to check that you are not anaemic because you will be having sedation and the anaesthetist will need to know that.

Should I do back-to-back cycles, or should I wait in between?

This depends on your AFC and AMH. If you have a high AMH it would probably be a good idea to have a break between cycles, but if you have a low or normal response, you could either do a “duostim” (dual stimulation) or a back-to-back cycle.

Should I spend 3 months preparing, or just freeze my eggs right away?

If you are in good health, don’t smoke/vape or drink excessively and have a reasonably good diet, you could freeze your eggs without preparing yourself for 3 months.

Answered by our in-house medical advisor.

Ovarian stimulation

Ovarian stimulation

Birth control and fertility medication

If you’re currently using hormonal birth control, you might need to stop taking it before the cycle begins. Other forms of birth control such as the IUD can be left in. Since hormonal birth control alters the natural level of hormones in the body, stopping it allows for natural baseline hormone levels to return and optimal follicle development during the stimulation phase.

During the stimulation phase, you’ll be administering injectable fertility medications to help with the growth and development of multiple follicles within your ovaries. Your doctor will provide detailed instructions on the specific medications, dosages, and injection techniques, ensuring safe and effective administration.

Medications you might come across

Illustration of a fertility medication syringe in its packaging

All the common injections contain FSH (follicle-stimulating hormone), which is needed to make the follicles grow. You may also need a small dose of luteinising hormone (LH) depending on your age and baseline hormone levels. Often these hormones are combined in a single injection. The trigger shot, taken near the end of the cycle, usually contains human chorionic gonadotropin (hCG), a hormone that helps the ovary mature and release an egg.

Gonal-FBemfolaFostimonPergoverisMeriofertMenopurOvitrelle (trigger shot)

Routine clinic visits

You’ll also need routine clinic visits throughout the medication phase. This is to do the prescribed blood tests and ultrasound to ensure that hormonal levels are working as predicted and to also check on follicle growth.

The follicle size is recorded as well with every visit to determine the timing for the trigger shot and the egg retrieval.

Questions to ask your doctor during ovarian stimulation

Will I have any side effects from the medication?

Most people don’t have any side effects at all other than the sensation of the follicles growing (fullness in the pelvis). If you notice any other side effects, contact your clinic.

Where do I inject these medications?

They are injected just under the skin, usually on your abdomen.

The injected area hurts due to multiple injections. Where else can I inject the medication?

You can inject it into your thighs, your upper arms or your buttocks.

What happens if I miss a dosage?

First of all, take a deep breath. If you’re panicking, we’re here to tell you: it’s not the end of the world. If you miss one dosage, just make sure to let your clinic know, so they can take the necessary steps.

Why might a doctor recommend that I need to take the hCG hormone?

The hCG hormone is usually given 36 hours before the egg collection and is essential for the eggs to mature and be freed from the follicle wall at the time of the egg collection.

Answered by our in-house medical advisor.

Egg retrieval

Trigger shot and egg retrieval

The trigger shot is given when one or multiple follicles reach a size of 16–22mm, where they are most likely to have an (almost) mature egg. An hCG trigger shot is given exactly 36 hours before the egg retrieval, such that the timing coincides with the maturity of the eggs.

How eggs are retrieved

Then comes the egg retrieval, which is a quick procedure of about 15 to 20 minutes where the gynaecologist uses a suction pump and a needle to directly retrieve the eggs from the right and left ovaries into a tube that is sent to the laboratory and the embryologists.

  • A trans-vaginal ultrasound probe is used to guide the needle into the follicle.
  • The needle enters the follicle and retrieves the egg. The egg travels down the aspirator (suction pipe) and into the media.

The night before the egg retrieval, you may be asked to avoid food and water intake until the egg retrieval is done, as you will be administered anaesthesia. Additionally, you may also be advised not to wear any jewellery, perfume, etc. to the operating theatre.

Questions to ask your doctor before egg retrieval

Should I be prepared in any way for the egg retrieval?

There’s no need to do any special preparation other than the necessary: abstaining from food and drink as discussed, due to anaesthesia given during the procedure.

What can I eat before and after egg retrieval?

You should not eat anything for several hours before your procedure and your clinic will give you precise instructions about this.

Answered by our in-house medical advisor.

Do’s and don’ts for recovering after your egg retrieval

Your doctor will provide specific instructions regarding pre-cycle activities and restrictions. You will be kept under observation for a couple of hours post-retrieval while you recover. You will then need to be taken home by a friend, partner or family member.

  • Avoid strenuous exercise: it’s probably best to avoid strenuous exercise until you are feeling completely back to normal. This may be a few days but can last until your next period arrives if you have a high response and many eggs are collected.
  • Avoid sexual activity (for just a while): it’s best to resume sexual activity a week or two after egg retrieval. This is to ensure that you get enough pelvic rest after the retrieval procedure. This also helps your body heal and prevent any infection.
  • Take painkillers if needed: you can take paracetamol or ibuprofen if you have any discomfort.
  • Watch out for side effects: some side effects of the egg-freezing medication could include constipation and a heavier period than usual. Try to increase fibre intake, hydrate well, and use heating pads or prescribed medication for pain relief.
  • Rest up: take the days post your egg retrieval solely for recovering and resting.
Setting expectations

Questions and expectations

Extra questions for your doctor

Don’t hesitate to ask your doctor any questions you might have about the process. Some key areas to clarify include:

  • Medication administration: ensure you fully understand the correct injection techniques, potential side effects, and storage requirements for fertility medications. You can get it administered by a nurse the first few times before getting the hang of it.
  • Egg number and quality: enquire about the typical range of egg retrieval numbers and the factors that influence egg quality.
  • Cost considerations: discuss the associated costs for the egg freezing cycle, including medication, procedures, and any potential additional expenses.
  • Cycle duration: get a realistic understanding of the expected timeline for your egg-freezing cycle, including the duration of the stimulation phase, the egg retrieval procedure, and the post-retrieval recovery period.

Setting expectations

We get it, preparing for your first egg-freezing cycle goes beyond the physical aspects. But completing it is a major milestone. It’s also important to clarify and set expectations for after your egg-freezing cycle. Here are some things to keep in mind.

1

Not all eggs will be mature

Even among the retrieved eggs, it’s great if all are mature, but there are chances that the number may vary. For instance, if the total number of follicles even on the day of egg retrieval is estimated to be 10, you may end up with 5 mature eggs, owing to the rest of the follicles containing immature eggs.

2

Egg retrieval number and follicle number aren’t the same

The retrieved number of eggs may be less than the number of follicles. For example, maybe you’ve had 15 follicles, but you may retrieve around 10 eggs. It is in fact a rare situation where the number of follicles exactly matches the number of eggs retrieved. It depends on the growth of the follicles in the ovaries and how mature the egg cell is, once it’s retrieved.

3

Not all eggs go into the same tank

Embryologists freeze about 2–3 eggs in a single cryostorage device and having more than this number may require additional devices. Nonetheless, your clinic will have secure measures to organise and store all your eggs safely.

I’m on my second cycle

I’ve already had an egg freezing cycle, and I’m on my second one. Is there anything I need to know?

Now that you’ve had some time to reflect, you might be feeling ready to embark on another cycle. We’ll explore how to approach your next cycle with fresh strategies and insights, ensuring the experience is even better this time around.

You may have a second egg-freezing cycle based on the results of your first one. You may have:

  • Retrieved fewer eggs during your first cycle.
  • Or your first cycle may have been cancelled due to early follicular rupture, risk of OHSS, etc.
  • Or, a second cycle was planned based on an egg pooling cycle, where you have back-to-back cycles to retrieve your eggs.

Based on the situation, your healthcare provider will adjust medication dosages or protocols based on your individual response and needs. We hope for you to have the right support and care around you, because, let’s face it: doing it all over isn’t easy.

But a second cycle is another chance at it. At retrieving more eggs, pooling better quality ones and ultimately for a chance at better success rates for your cycle.

What you can do differently

1

Ask more questions

Don’t hesitate to ask your doctor detailed questions about the specific medications, dosages, and potential risks associated with OHSS (ovarian hyperstimulation syndrome). Comparing your previous experience with the current cycle allows you to be more informed and understand any adjustments in the cycle or the medications better.

2

Clinic evaluation

If you’re considering a different clinic for your second cycle, thoroughly research their reported success rates, patient testimonials, and overall clinic environment. Ensure it aligns with your needs and preferences for a comfortable and positive experience.

“If I were to do another cycle again, I’d be way more inquisitive and ask more questions about the medications. When I did my cycle, I always wondered whether I really needed a lower or higher dose, why they picked certain drugs for me, and if a medication would make me more or less bloated. I just wanted to know what I was injecting into my body! I would also prepare better by drinking less alcohol than usual, and creating a better mindset because I did the cycle quite spontaneously.”

Sarita Stefani, CEO and co-founder of Amilis, froze her eggs at 32

After a failed cycle

I’ve had a failed egg freezing cycle and this is my next attempt. How do I prepare?

Facing a failed egg-freezing cycle is tough, and it’s important to acknowledge the emotions that come with it. Here, we’ll focus on finding acceptance and moving forward with resilience, with ways to support yourself both mentally and physically.

We’re so proud of you to have come this far. Experiencing a failed egg-freezing cycle can be emotionally challenging. There are many reasons for a failed egg-freezing cycle.

And it’s okay to be frustrated, sad or to let it out. There’s a burden of lost time and effort, and it’s normal for you to feel the physical and mental toll of it.

Rather, in the event of an egg-freezing failure it’s best to focus on what worked, and what didn’t, and figure out an alternative to the same. Most often, the next step after a failed egg-freezing cycle is one that’s curated and personalised to avoid any hiccups in the next cycle.

We’ve listed some ways to prepare yourself mentally and physically after a failed egg-freezing cycle.

Seeking support

  • Connect with others: joining online communities or support groups that have individuals who went through similar experiences can provide emotional support and a sense of belonging. You can share your journey, journal, and connect with others who understand your challenges, as it can help foster resilience and emotional well-being.
  • Mental health support: consider exploring mindfulness practices, relaxation techniques, or therapy to manage any emotional challenges associated with your previous experience. Prioritising your mental health and emotional well-being should be on the checklist for your next cycle.
  • Discuss your feelings with your doctor: this honest communication allows them to address your concerns, provide additional support, and potentially adjust the treatment plan and duration based on your individual needs and emotional state.

Focusing on your health

  • Healthy diet: focus on incorporating a balanced and nutritious diet rich in fruits, vegetables, whole grains, and lean protein. This provides your body with the essential nutrients it needs to support optimal egg quality and overall health.
  • Regular exercise: engaging in regular physical activity can significantly contribute to physical and mental well-being. Exercise helps manage stress and improve sleep quality, and thus your overall health.
  • Stress management: prioritise stress-reduction techniques like yoga, meditation, or deep breathing exercises. Managing stress effectively can create a more favourable hormonal environment.

6 affirmations for your egg freezing journey

These affirmations can help you stay positive and focused throughout your egg freezing journey.

I am taking proactive steps towards my future fertility goals.

I trust my body and the medical professionals guiding me.

I am strong, capable, and resilient.

I am surrounded by love and support.

I am confident in my decision to freeze my eggs.

I am excited about the possibilities that lie ahead.

And here’s one from Amilis: we believe in you. You’re making proactive choices for your reproductive health, and we’re here to support you, every step of the way!

Where Amilis comes in

Whether you’re researching egg freezing or preparing for your first or second cycle, we’ve met the clinics and specialists, we show you what one cycle really costs, and most offer a free 15-minute call before you decide anything.

Two friends hugging and laughing

Free guide · 31 pages · Written with fertility specialists

Preparing for egg freezing

Wherever you are in your journey, from first wondering about egg freezing to your first, second or next cycle, this guide is here to answer your questions on all things egg freezing. About 22 minutes to read.

No email, no sign-up.

Chapter 1

Introduction

Egg freezing has become quite the talk of the town. With celebrities doing it, news reports and magazines covering it, and people sharing their experiences on it, you’re left to wonder: what’s all this about?

It may sound intimidating, the talk around fertility, testing, appointments, the process. But we’re here to tell you: it’s only because it’s not talked about enough.

The point is: egg freezing is not just a hushed topic anymore. It’s a reproductive choice.

It’s for women who want to voluntarily preserve their fertility. It’s for the LGBTQ community, to freeze eggs or go for donor eggs to start their family. It’s a mandatory task for women undergoing chemotherapy. It’s advised for women before their endometriosis surgery.

And regardless of where you are in your journey, be it your first cycle, or last, this guide is here to answer your questions, on all things egg freezing.

So, grab that cup of coffee and read on!

Medically reviewed by Dr Vivienne Hall, Fertility Specialist.

Chapter 2

New to egg freezing

Welcome to the “our reproductive choices, our own terms” club.

Apart from that, it’s also about what’s not discussed enough: that there is a natural decline in fertility with our age. As we hit our late 20s and 30s, the number and the quality of eggs in our ovaries begin to decline. And rather than panic about it, it’s time to sit back and think about your reproductive health.

Are you okay with not having a family in the future, or are you in the “maybe” or “thinking about it” boat? That’s where egg freezing comes in.

The egg freezing process in the UK

Egg freezing helps you save a number of eggs at good quality for fertilisation and family planning later on (AKA, when you’re ready to start a family). That’s right. No partner. No need for a sperm donor. Just you and your health choices.

It involves a series of blood tests that check your hormonal levels. Post that, you undergo a week or two of hormonal medication that helps grow multiple eggs in your ovaries (versus the normal “one egg of the month”). As the last step, you undergo egg retrieval, where they aspirate and freeze your eggs in the laboratory, done by embryologists.

1 · Initial consultation

Discussing your individual circumstances, goals and expectations with a qualified fertility specialist. This initial meeting is important as it helps your healthcare provider curate a personalised plan and address any specific concerns you might have.

2 · Medical evaluation

You may be tested for hormones such as anti-Müllerian hormone (AMH), which helps you assess egg reserve, ultrasound tests such as antral follicle count, and hormones such as FSH and LH to assess your ovarian reserve and overall fertility health. These tests provide valuable insights into your egg quantity and quality, informing the most suitable approach for your individual needs.

3 · Stimulation phase

Fertility medications are administered to stimulate the development of multiple eggs within your ovaries. This phase typically involves daily injections such as gonadotropins for a specific duration, as determined by your doctor based on your individual response and the overall treatment plan. The final step of the stimulation plan is the trigger (hCG), which is given 36 hours before egg retrieval. This helps mature the egg right in time for retrieval.

4 · Egg retrieval procedure

A minimally invasive procedure performed under light sedation or anaesthesia to collect mature eggs for freezing. This brief procedure allows gynaecologists to puncture the follicle and extract the eggs from the ovaries, which are then sent to the laboratory for further processes.

5 · Cryopreservation

The retrieved eggs are frozen using vitrification techniques for long-term storage. One such device used to freeze is called a cryolock, which is a thin device with a cap. One cryolock can hold about 2–3 eggs. This process effectively preserves the eggs, by dipping the cryolocks in liquid nitrogen containers, allowing them to be thawed and used for future fertilisation attempts when you’re ready to use them.

What if I want to use my frozen eggs?

When you’re ready to use your frozen eggs, you just have to give the clinic a call. You will then be tested for hormones, and based on your stage of the menstrual cycle, your healthcare provider will personalise an embryo transfer protocol for you.

We like to split this part into two stages:

  • The laboratory stage: this involves several crucial steps when it comes to identifying and preparing the egg for intracytoplasmic sperm injection (ICSI).
  • The embryo transfer stage: this refers to the steps taken from preparing the uterus to transferring the embryo and confirming a pregnancy.

The laboratory stage

  • You may ask to use your frozen eggs if you have a sperm donor sample or your partner’s sperm sample.
  • The embryologist identifies the cryolock that has your frozen eggs, and prepares to warm them.
  • After that, each egg is fertilised with one sperm to create an embryo via ICSI (intracytoplasmic sperm injection) and not IVF (in vitro fertilisation).

Why ICSI instead of IVF?

IVF mimics natural fertilisation in a way, but happens in the lab, where eggs and sperm are incubated together in media overnight, and checked for fertilisation. During IVF, the eggs are left intact with the cells around them, which play a key role in allowing only one sperm to fertilise the egg, just as it happens naturally.

But with frozen eggs, the cells outside the egg are removed before freezing. Once the egg is “nude” or stripped of its protective jacket, you risk multiple sperm entering the egg if IVF were to be done. To avoid that, ICSI is done, such that one sperm is injected at a time.

The embryo transfer stage

  • At this stage, the embryo is at day 5/6/7. Most clinics transfer day 5 embryos, and day 6 or day 7 embryos can be frozen for future use.
  • By now, you would have ideally had a medicated protocol to prepare your uterus for this transfer. The medication is to ensure that the uterine lining is thick and supportive of this new member (the embryo).
  • The gynaecologist takes a flexible, smooth device called a catheter to insert the embryo into the uterus (around the fundus).
  • And next? We hope for implantation to occur and for the embryo to be nested in its cosy new home.

Around 15 days later, you may be asked to take a beta hCG test, to confirm pregnancy.

Chapter 3

Exploring your options

You’ve done your homework, given it a lot of thought, and now you’re curious about how to start exploring egg freezing. The decision-making process can be overwhelming, perplexing, and even daunting.

Do I consult my GP? Should I book an appointment online? Should I search around for the best fertility clinic? This is where Sophie Hermann found herself too, at one point:

“So here I was at 36, still mulling over this decision. I’d been wrestling with these thoughts for a good four years. The big questions were: Where do I start? How long will it take? What’s the cost? And let’s not forget the big one – is it going to hurt?” – Sophie Hermann, 36

Understanding your egg reserve

Understanding your egg reserve and hormonal levels is the first step in the egg-freezing process.

Our ovaries contain follicles which help house, grow and mature eggs every month. These growing follicles produce anti-Müllerian hormone (AMH), which can be measured via a simple blood test.

This helps provide valuable insights into your ovarian reserve, helping your healthcare provider or GP gauge your egg yield number or reserve and the potential steps to take if you opt for an egg-freezing cycle.

1-1 consultations

A 1-1 consultation is an interactive session that allows you to ask questions, discuss your individual circumstances, and receive tailored guidance. This can help you decide on whether egg freezing is for you or not, and provide clarity as you move forward.

Choosing a clinic

With so many options out there, it can be overwhelming to find the one that fits your needs. How do you choose the right clinic out of so many options? Is it worth switching if you’re not getting on with your current fertility doctor? Here are some factors to consider when choosing an egg freezing clinic.

Clear success rates

We suggest learning about different types of success rates, and understanding how different clinics talk about their success rates. You’ll see “live birth rates” used regularly as this is the end goal most women are thinking of.

Location

Often several visits are needed as part of a treatment, so make sure the clinic’s location is convenient.

Cost

You might be able to afford the top fertility clinic, regardless of price. Or you may be on a tighter budget. Either way, cost vs quality is a key point to think about. For today’s real prices at the clinics we’ve met, see Compare prices →

Your instinct

Don’t forget, choosing a fertility clinic is a personal decision. What works for someone else may not work for you. Do your research. Trust your instincts.

Staff and facilities

Knowledgeable and caring staff make all the difference. It’s a lot easier to talk about fertility when you feel comfortable. Kind, qualified clinic staff and modern, up-to-date facilities will give you a better overall experience.

Services offered

Whilst choosing a location to freeze and store your eggs, it’s helpful to know whether they offer intracytoplasmic sperm injection (ICSI), the technique used to fertilise frozen eggs when the time comes.

Your next step

Choosing a clinic?

Start with a free 15-minute call with a couple of clinics you like, then compare what’s included and the real total.

Chapter 4

Medical evaluation

It can be scary to think about all that is to come, but we want to remind you that you’re doing this for future you. And that you’ve got this.

At this stage, you’ve had a chat with your GP, visited a clinic, decided that egg freezing is for you, and are at the first step of your egg freezing cycle. Here is a deep dive of the first step.

1 · Hormone testing

Your doctor will likely recommend hormone testing, including anti-Müllerian hormone (AMH) and follicle-stimulating hormone (FSH) levels. These tests help provide valuable insights into your ovarian reserve, helping your healthcare provider decide the most suitable approach for your individual needs.

2 · Ultrasound scans

Pelvic ultrasounds are often used to assess the antral follicle count (AFC), which reflects the number of small follicles in your ovaries that have the potential to develop into mature eggs. This information, combined with your hormone levels, helps your doctor personalise the stimulation protocol for your cycle.

3 · Cycle preparation

Discuss with your doctor whether a 3-month pre-cycle preparation period is recommended or if you can get started straight away.

Questions to ask your doctor during your medical evaluation

Answered by our in-house medical advisor.

What does it mean if my AFC is low or high?

Antral follicle count (AFC) is basically an ultrasound visualisation of the number of follicles on the surface of the ovary that month.

A group of follicles every month are selected to release the “egg of the month”, and a high or low AFC means the same as a high or low AMH because it is the pre-antral follicles which produce AMH.

So a low AFC indicates a low egg reserve and a high AFC might be described as a polycystic ovary.

What does it mean if my AMH is low or high?

If your AMH (anti-Müllerian hormone) is low, it usually indicates a declining egg reserve (low number of eggs left in your ovaries).

If your AMH is high (in cases such as PCOS) it could mean that you retrieve more eggs during an egg freezing cycle, but it is also a risk factor for conditions such as OHSS.

Does my follicle number mean that I get the same number of eggs?

As a general rule, the antral follicle count is a good indicator of the number of eggs you will get.

To be precise, when undergoing stimulation for egg freezing, you may be given an estimate of follicles that are in the 16–22mm range, which are said to be more indicative of having a mature egg.

Why do I need routine blood tests as well?

You need routine blood tests including virology screening because your eggs will be stored in a laboratory. Any human tissue or sample being handled and kept in storage has these legal requirements to be screened for hepatitis B, C and also HIV.

You will also have a full blood count to check that you are not anaemic because you will be having sedation and the anaesthetist will need to know that.

Should I do back-to-back cycles, or should I wait in between?

This depends on your AFC and AMH. If you have a high AMH it would probably be a good idea to have a break between cycles, but if you have a low or normal response, you could either do a “duostim” (dual stimulation) or a back-to-back cycle.

Should I spend 3 months preparing, or just freeze my eggs right away?

If you are in good health, don’t smoke/vape or drink excessively and have a reasonably good diet, you could freeze your eggs without preparing yourself for 3 months.

Chapter 5

Ovarian stimulation

Birth control and fertility medication

If you’re currently using hormonal birth control, you might need to stop taking it before the cycle begins. Other forms of birth control such as the IUD can be left in. Since hormonal birth control alters the natural level of hormones in the body, stopping it allows for natural baseline hormone levels to return and optimal follicle development during the stimulation phase.

During the stimulation phase, you’ll be administering injectable fertility medications to help with the growth and development of multiple follicles within your ovaries. Your doctor will provide detailed instructions on the specific medications, dosages, and injection techniques, ensuring safe and effective administration.

Medications you might come across

All the common injections contain FSH (follicle-stimulating hormone), which is needed to make the follicles grow. You may also need a small dose of luteinising hormone (LH) depending on your age and baseline hormone levels. Often these hormones are combined in a single injection. The trigger shot, taken near the end of the cycle, usually contains human chorionic gonadotropin (hCG), a hormone that helps the ovary mature and release an egg.

  • Gonal-F
  • Bemfola
  • Fostimon
  • Pergoveris
  • Meriofert
  • Menopur
  • Ovitrelle (trigger shot)

Routine clinic visits

You’ll also need routine clinic visits throughout the medication phase. This is to do the prescribed blood tests and ultrasound to ensure that hormonal levels are working as predicted and to also check on follicle growth.

The follicle size is recorded as well with every visit to determine the timing for the trigger shot and the egg retrieval.

Questions to ask your doctor during ovarian stimulation

Answered by our in-house medical advisor.

Will I have any side effects from the medication?

Most people don’t have any side effects at all other than the sensation of the follicles growing (fullness in the pelvis). If you notice any other side effects, contact your clinic.

Where do I inject these medications?

They are injected just under the skin, usually on your abdomen.

The injected area hurts due to multiple injections. Where else can I inject the medication?

You can inject it into your thighs, your upper arms or your buttocks.

What happens if I miss a dosage?

First of all, take a deep breath. If you’re panicking, we’re here to tell you: it’s not the end of the world. If you miss one dosage, just make sure to let your clinic know, so they can take the necessary steps.

Why might a doctor recommend that I need to take the hCG hormone?

The hCG hormone is usually given 36 hours before the egg collection and is essential for the eggs to mature and be freed from the follicle wall at the time of the egg collection.

Chapter 6

Trigger shot and egg retrieval

The trigger shot is given when one or multiple follicles reach a size of 16–22mm, where they are most likely to have an (almost) mature egg. An hCG trigger shot is given exactly 36 hours before the egg retrieval, such that the timing coincides with the maturity of the eggs.

How eggs are retrieved

Then comes the egg retrieval, which is a quick procedure of about 15 to 20 minutes where the gynaecologist uses a suction pump and a needle to directly retrieve the eggs from the right and left ovaries into a tube that is sent to the laboratory and the embryologists.

  • A trans-vaginal ultrasound probe is used to guide the needle into the follicle.
  • The needle enters the follicle and retrieves the egg. The egg travels down the aspirator (suction pipe) and into the media.

The night before the egg retrieval, you may be asked to avoid food and water intake until the egg retrieval is done, as you will be administered anaesthesia. Additionally, you may also be advised not to wear any jewellery, perfume, etc. to the operating theatre.

Questions to ask your doctor before egg retrieval

Answered by our in-house medical advisor.

Should I be prepared in any way for the egg retrieval?

There’s no need to do any special preparation other than the necessary: abstaining from food and drink as discussed, due to anaesthesia given during the procedure.

What can I eat before and after egg retrieval?

You should not eat anything for several hours before your procedure and your clinic will give you precise instructions about this.

Do’s and don’ts for recovering after your egg retrieval

Your doctor will provide specific instructions regarding pre-cycle activities and restrictions. You will be kept under observation for a couple of hours post-retrieval while you recover. You will then need to be taken home by a friend, partner or family member.

  • Avoid strenuous exercise: it’s probably best to avoid strenuous exercise until you are feeling completely back to normal. This may be a few days but can last until your next period arrives if you have a high response and many eggs are collected.
  • Avoid sexual activity (for just a while): it’s best to resume sexual activity a week or two after egg retrieval. This is to ensure that you get enough pelvic rest after the retrieval procedure. This also helps your body heal and prevent any infection.
  • Take painkillers if needed: you can take paracetamol or ibuprofen if you have any discomfort.
  • Watch out for side effects: some side effects of the egg-freezing medication could include constipation and a heavier period than usual. Try to increase fibre intake, hydrate well, and use heating pads or prescribed medication for pain relief.
  • Rest up: take the days post your egg retrieval solely for recovering and resting.

Chapter 7

Questions and expectations

Extra questions for your doctor

Don’t hesitate to ask your doctor any questions you might have about the process. Some key areas to clarify include:

  • Medication administration: ensure you fully understand the correct injection techniques, potential side effects, and storage requirements for fertility medications. You can get it administered by a nurse the first few times before getting the hang of it.
  • Egg number and quality: enquire about the typical range of egg retrieval numbers and the factors that influence egg quality.
  • Cost considerations: discuss the associated costs for the egg freezing cycle, including medication, procedures, and any potential additional expenses.
  • Cycle duration: get a realistic understanding of the expected timeline for your egg-freezing cycle, including the duration of the stimulation phase, the egg retrieval procedure, and the post-retrieval recovery period.

Setting expectations

We get it, preparing for your first egg-freezing cycle goes beyond the physical aspects. But completing it is a major milestone. It’s also important to clarify and set expectations for after your egg-freezing cycle. Here are some things to keep in mind.

Not all eggs will be mature

Even among the retrieved eggs, it’s great if all are mature, but there are chances that the number may vary. For instance, if the total number of follicles even on the day of egg retrieval is estimated to be 10, you may end up with 5 mature eggs, owing to the rest of the follicles containing immature eggs.

Egg retrieval number and follicle number aren’t the same

The retrieved number of eggs may be less than the number of follicles. For example, maybe you’ve had 15 follicles, but you may retrieve around 10 eggs. It is in fact a rare situation where the number of follicles exactly matches the number of eggs retrieved. It depends on the growth of the follicles in the ovaries and how mature the egg cell is, once it’s retrieved.

Not all eggs go into the same tank

Embryologists freeze about 2–3 eggs in a single cryostorage device and having more than this number may require additional devices. Nonetheless, your clinic will have secure measures to organise and store all your eggs safely.

Chapter 8

Your second cycle

Now that you’ve had some time to reflect, you might be feeling ready to embark on another cycle. We’ll explore how to approach your next cycle with fresh strategies and insights, ensuring the experience is even better this time around.

You may have a second egg-freezing cycle based on the results of your first one. You may have:

  • Retrieved fewer eggs during your first cycle.
  • Or your first cycle may have been cancelled due to early follicular rupture, risk of OHSS, etc.
  • Or, a second cycle was planned based on an egg pooling cycle, where you have back-to-back cycles to retrieve your eggs.

Based on the situation, your healthcare provider will adjust medication dosages or protocols based on your individual response and needs. We hope for you to have the right support and care around you, because, let’s face it: doing it all over isn’t easy.

But a second cycle is another chance at it. At retrieving more eggs, pooling better quality ones and ultimately for a chance at better success rates for your cycle.

1 · Ask more questions

Don’t hesitate to ask your doctor detailed questions about the specific medications, dosages, and potential risks associated with OHSS (ovarian hyperstimulation syndrome). Comparing your previous experience with the current cycle allows you to be more informed and understand any adjustments in the cycle or the medications better.

2 · Clinic evaluation

If you’re considering a different clinic for your second cycle, thoroughly research their reported success rates, patient testimonials, and overall clinic environment. Ensure it aligns with your needs and preferences for a comfortable and positive experience.

“If I were to do another cycle again, I’d be way more inquisitive and ask more questions about the medications. When I did my cycle, I always wondered whether I really needed a lower or higher dose, why they picked certain drugs for me, and if a medication would make me more or less bloated. I just wanted to know what I was injecting into my body! I would also prepare better by drinking less alcohol than usual, and creating a better mindset because I did the cycle quite spontaneously.” – Sarita Stefani, CEO & Co-Founder of Amilis, froze her eggs at 32

Chapter 9

After a failed cycle

Facing a failed egg-freezing cycle is tough, and it’s important to acknowledge the emotions that come with it. Here, we’ll focus on finding acceptance and moving forward with resilience, with ways to support yourself both mentally and physically.

We’re so proud of you to have come this far. Experiencing a failed egg-freezing cycle can be emotionally challenging. There are many reasons for a failed egg-freezing cycle.

And it’s okay to be frustrated, sad or to let it out. There’s a burden of lost time and effort, and it’s normal for you to feel the physical and mental toll of it.

Rather, in the event of an egg-freezing failure it’s best to focus on what worked, and what didn’t, and figure out an alternative to the same. Most often, the next step after a failed egg-freezing cycle is one that’s curated and personalised to avoid any hiccups in the next cycle.

We’ve listed some ways to prepare yourself mentally and physically after a failed egg-freezing cycle.

Seeking support

  • Connect with others: joining online communities or support groups that have individuals who went through similar experiences can provide emotional support and a sense of belonging. You can share your journey, journal, and connect with others who understand your challenges, as it can help foster resilience and emotional well-being.
  • Mental health support: consider exploring mindfulness practices, relaxation techniques, or therapy to manage any emotional challenges associated with your previous experience. Prioritising your mental health and emotional well-being should be on the checklist for your next cycle.
  • Discuss your feelings with your doctor: this honest communication allows them to address your concerns, provide additional support, and potentially adjust the treatment plan and duration based on your individual needs and emotional state.

Focusing on your health

  • Healthy diet: focus on incorporating a balanced and nutritious diet rich in fruits, vegetables, whole grains, and lean protein. This provides your body with the essential nutrients it needs to support optimal egg quality and overall health.
  • Regular exercise: engaging in regular physical activity can significantly contribute to physical and mental well-being. Exercise helps manage stress and improve sleep quality, and thus your overall health.
  • Stress management: prioritise stress-reduction techniques like yoga, meditation, or deep breathing exercises. Managing stress effectively can create a more favourable hormonal environment.

6 affirmations for your egg freezing journey

These affirmations can help you stay positive and focused throughout your egg freezing journey.

  • I am taking proactive steps towards my future fertility goals.
  • I am confident in my decision to freeze my eggs.
  • I trust my body and the medical professionals guiding me.
  • I am excited about the possibilities that lie ahead.
  • I am surrounded by love and support.
  • I am strong, capable, and resilient.

And here’s one from Amilis: we believe in you. You’re making proactive choices for your reproductive health, and we’re here to support you, every step of the way!

Your next step

Choosing a clinic?

Start with a free 15-minute call with a couple of clinics you like, then compare what’s included and the real total.
